A new study trained an AI model on 24,000+ electronic health records (EHRs) to predict whether a patient would develop schizophrenia or bipolar disorder. The results? 🤔
🔍 The XGBoost machine learning model showed better performance for schizophrenia than bipolar disorder. 📊 It achieved an AUC of 0.70 on training data and 0.64 on the test set. ⚠️ But here’s the catch: despite 96.3% specificity, the model’s sensitivity was just 9.3%, meaning it missed the vast majority of cases.
💡 Bottom Line: AI in psychiatry is promising, but we’re not at the point where a model like this could reliably flag patients at risk. High specificity sounds great—until you realize the trade-off is missing 90%+ of those who actually transition to schizophrenia or bipolar disorder.
Will future AI tools get better at predicting these life-altering conditions? Time (and data) will tell. ⏳
A new study sheds light on suicide risk in patients with psychotic disorders, comparing those with recent-onset schizophrenia or other psychotic disorders to those with longer illness duration. The findings offer critical insights for clinicians and mental health professionals.
🚨 Key Takeaways:
📌 Early Illness = Higher Risk: Patients within the first five years of their illness had higher suicide rates, emphasizing the need for intensive early intervention.
📌 Common Risk Factors: Across both groups, depression, prior suicide attempts, and substance use were major red flags.
📌 Different Patterns: Those with recent-onset psychosis were more likely to have rapid illness progression, while those with longer illness duration often had chronic distress and social isolation before suicide.
📌 Missed Opportunities? Many had recent healthcare encounters before suicide, highlighting potential gaps in risk assessment and intervention.
🛑 What This Means for Us: 🔹 Early-phase psychosis care should prioritize suicide prevention. 🔹 Screening for depression, substance use, and prior attempts is essential. 🔹 More proactive intervention is needed, especially after hospital visits.
This study reinforces what many frontline clinicians already suspect—suicide prevention in psychosis requires urgent, tailored strategies. How can we improve early detection and support for at-risk patients? Let’s discuss. 👇
A groundbreaking study just dropped in JAMA Psychiatry, shedding light on the link between cannabis use disorder (CUD) and schizophrenia following cannabis legalization.
📊 Key Findings:
Higher rates of schizophrenia diagnoses were observed in young men with CUD after legalization.
The association was strongest in males aged 18–24, a group already at high risk for schizophrenia onset.
No significant changes were found in individuals without CUD, reinforcing concerns about cannabis as a potential trigger in vulnerable populations.
🧠 What This Means: Cannabis legalization doesn’t just increase access—it may be shifting the trajectory of severe mental illness in at-risk groups. While correlation ≠ causation, this study adds weight to the argument that heavy cannabis use isn’t harmless, especially for young people with genetic or neurodevelopmental vulnerabilities.
⚖️ Clinical & Policy Implications:
Should we rethink cannabis policy in light of these findings?
Do we need stronger public health messaging about the psychiatric risks of heavy cannabis use?
How can we better screen and intervene early for CUD in young men?
As psychiatrists, we see these cases firsthand—the young man with new-onset psychosis, the family blindsided, the struggle to regain lost cognitive and social function.
This study is a wake-up call. Legal ≠ safe for everyone.
What are your thoughts? Should legalization come with more psychiatric safeguards? Drop your insights below. ⬇️
📢 Update on Schizophrenia Research #MentalHealth #Schizophrenia
🧠 Iclepertin (BI 425809), initially showing promise in Phase II trials, unfortunately did not meet the primary and key secondary endpoints in the Phase III CONNEX program. Despite this, it was well tolerated, and the safety profile remained consistent.
🔬 Phase III Results:
No statistically significant improvements in cognition or functioning were observed compared to placebo over six months.
Context: Iclepertin is a glycine transporter 1 (GlyT1) inhibitor, a class of drugs aimed at enhancing the function of the NMDA receptor by increasing glycine levels. This receptor plays a crucial role in cognitive processes, and improving its function was hypothesized to alleviate cognitive impairments in schizophrenia.
📊 Visual Insights: Below are graphs illustrating the trial data, showing the comparison between Iclepertin and placebo groups across various cognitive assessments.
🔍 Implications and Next Steps: Although these results are disappointing, they provide valuable insights for future research. The findings highlight the complexity of treating cognitive impairment in schizophrenia and underscore the need for continued exploration of new therapeutic targets and strategies.
What’s next? Researchers will analyze the data further to identify any subgroups that may have benefited and explore other potential mechanisms to address this unmet medical need.
💬 Join the Discussion: Have you or someone you know experienced cognitive challenges related to schizophrenia? What are your thoughts on current treatment options? Share your experiences or questions below—let’s foster a supportive community!
🔔 Stay Updated: Follow us for more updates on ongoing research and join our forums for in-depth discussions on mental health innovations. Together, we can stay informed and connected. #ClinicalTrials #Neuroscience #Breakthrough
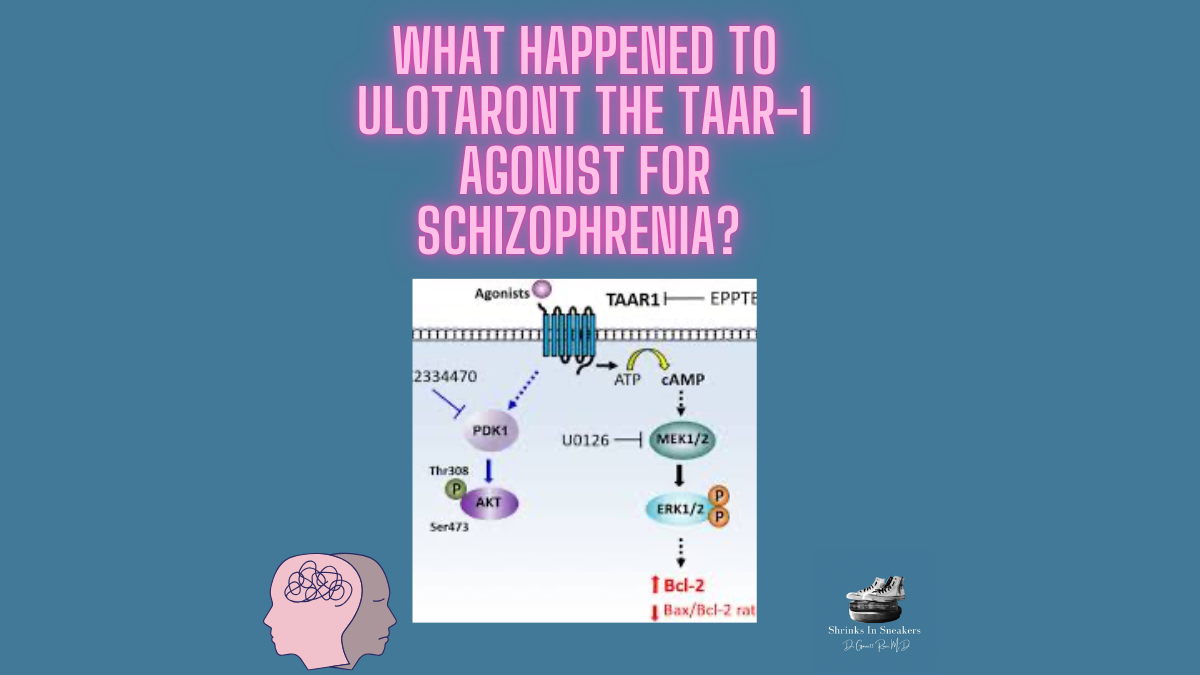
Back in 2019, during my residency, TAAR-1 agonists were hailed as the future of schizophrenia treatment, generating a wave of excitement and high expectations. Fast forward to 2025, and the once-prominent buzz has all but vanished. What happened to this promising class of drugs that once seemed poised to revolutionize the field?
Ulotaront, an investigational antipsychotic developed by Sumitomo Pharma and Otsuka Pharmaceutical, has recently encountered significant challenges in its clinical development. In July 2023, the drug failed to meet primary endpoints in two Phase III clinical trials aimed at treating acutely psychotic adults with schizophrenia. These studies did not demonstrate a statistically significant improvement over placebo, raising concerns about ulotaront’s efficacy in this patient population.
Given these setbacks, the timeline for ulotaront’s potential approval by the U.S. Food and Drug Administration (FDA) is now uncertain.Consequently, any previous projections for FDA approval will likely be delayed as the developers reassess their clinical strategy.
It’s important to note that ulotaront had previously received Breakthrough Therapy Designation from the FDA in 2019 for the treatment of schizophrenia, reflecting initial optimism about its therapeutic potential.
This post is inspired by a real case from my practice involving a patient with no significant past psychiatric history but a strong history of substance use, including opioids and cocaine. The patient had been on buprenorphine maintenance therapy for several decades, providing stability in their recovery. However, following an abrupt discontinuation of buprenorphine, the patient developed acute psychotic symptoms. This case highlights an uncommon but important phenomenon clinicians should be aware of when managing buprenorphine discontinuation, especially in individuals with a history of substance use.
Emerging evidence suggests that abrupt discontinuation of buprenorphine may induce psychosis in some individuals, though this appears to be a relatively uncommon occurrence. Here are the key findings:
Documented Cases
New-onset psychotic symptoms have been reported after sudden cessation of buprenorphine in patients with no prior psychosis.
Common symptoms include auditory hallucinations, paranoid ideation, and delusions of reference.
Psychotic symptoms typically emerge within days to weeks after discontinuation.
Potential Mechanisms
Loss of buprenorphine’s antipsychotic effects through kappa-opioid receptor antagonism.
Interaction between neurobiological vulnerabilities and the stress of withdrawal.
Symptoms may resolve in weeks to months, though some cases persist longer.
Reintroduction of buprenorphine has led to symptom remission in some cases, suggesting a causal relationship.
Gradual tapering of buprenorphine might mitigate this risk, though more research is needed.
Clinical Implications
Clinicians should remain vigilant when discontinuing buprenorphine, especially in individuals with risk factors for psychosis. A gradual tapering strategy is recommended to reduce potential risks, though further studies are necessary to guide best practices.
Understanding this phenomenon highlights the importance of individualized care when managing buprenorphine discontinuation in vulnerable populations.
Research into the therapeutic potential of cannabis for mental health disorders has grown in recent years, with mixed findings from randomized controlled trials (RCTs).
Anxiety Disorders
CBD (Cannabidiol) has shown promise in reducing anxiety symptoms in RCTs, particularly for social anxiety disorder (SAD). For instance, a small RCT found that a single dose of 300 mg of CBD reduced anxiety levels in participants undergoing a simulated public speaking test.
Some RCTs suggest that CBD may be anxiolytic without causing impairment or euphoria, making it preferable for anxiety compared to THC-dominant cannabis products, which may exacerbate anxiety in some users.
Post-Traumatic Stress Disorder (PTSD)
RCTs exploring THC and CBD combinations in PTSD have had mixed outcomes. Some studies indicate that THC may reduce nightmares and improve sleep in PTSD patients, though these findings are generally based on small sample sizes and short-term trials.
A recent RCT with a synthetic cannabinoid (nabilone) reported some symptom improvement in PTSD-related insomnia and nightmares. However, larger trials with longer follow-ups are necessary to clarify the efficacy and safety for PTSD.
Depression
Few RCTs show consistent evidence supporting cannabis (CBD or THC) as an effective treatment for major depressive disorder. Some trials indicate that CBD may have antidepressant-like effects, possibly due to serotonin receptor activity, but more robust and long-term studies are needed.
Concerns persist over THC’s potential to exacerbate depressive symptoms, particularly with regular or heavy use.
Schizophrenia and Psychotic Disorders
THC-dominant products have been associated with increased risk of psychosis and exacerbation of symptoms in people predisposed to psychotic disorders. This has led to caution against THC use in people with schizophrenia.
CBD has shown promise as an adjunctive treatment in some RCTs, with findings suggesting that it may have antipsychotic effects without the psychoactive effects of THC. For example, an RCT found that CBD reduced psychotic symptoms and improved cognitive function when added to standard antipsychotic treatment, though the effects were modest.
Bipolar Disorder
Evidence from RCTs on the use of cannabis in bipolar disorder is sparse and generally negative. Some trials indicate that THC may worsen manic and depressive symptoms in bipolar patients, and there is little to no support for cannabis as a treatment for bipolar depression.
Sleep Disorders
Some RCTs have evaluated cannabinoids for sleep disturbances, with CBD showing potential for improving sleep quality. However, THC may reduce REM sleep, which could impact sleep architecture negatively over time.
For PTSD-related insomnia, cannabinoids like nabilone have shown some benefit, but the effects on sleep in general populations remain uncertain.
Limitations
Sample Sizes and Duration: Many RCTs are small and short-term, limiting the generalizability and understanding of long-term effects.
Dosing and Formulations: Variability in cannabinoid content (THC vs. CBD), formulations (edibles, oils, vapes), and dosages across studies makes comparison challenging.
Side Effects: Both CBD and THC can have side effects, though THC’s psychoactive properties can lead to cognitive impairment, addiction potential, and negative impact on mood in some patients.
While CBD shows some promise in anxiety, PTSD, and psychotic disorders, RCT evidence for other mental health conditions remains inconclusive or even negative, especially with THC. Further large-scale, long-term RCTs are needed to establish the efficacy and safety profile of cannabis-based treatments in mental health.
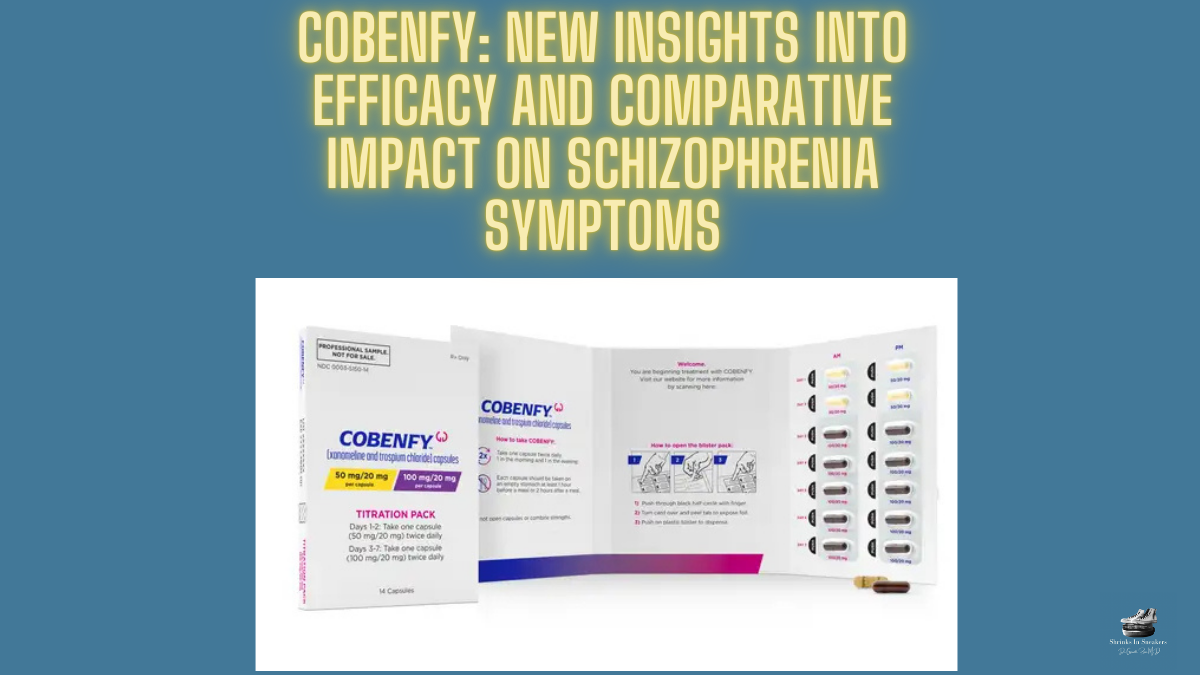
Effect Size: Cobenfy’s overall efficacy on the Positive and Negative Syndrome Scale (PANSS) stands at an effect size of 0.6, which is higher than many established antipsychotics (typically 0.3-0.5). However, clozapine still leads as the gold standard, with effect sizes ranging from 0.76 to 1.0.
NNT (Number Needed to Treat): The estimated NNT for Cobenfy is around 4, placing it in the mid-range among antipsychotics, where NNTs often range from 3 to 10.
Negative Symptom Impact
Cobenfy shows a notable efficacy in reducing negative symptoms. It achieves an impressive effect size of 1.18for this symptom domain, which is uncommon among antipsychotics. This improvement in negative symptoms appears to be independent of reductions in positive symptoms, a distinct advantage over traditional agents.
The NNT for negative symptoms specifically is around 2, highlighting Cobenfy’s potential as a robust option for patients struggling with these challenging symptoms.
Onset of Action
Rapid Onset: Cobenfy begins to show statistically significant improvements by week 3.
Peak Effect: Maximal symptom improvement is typically observed by week 5.
Conclusion Cobenfy offers strong efficacy in schizophrenia, with unique advantages for negative symptoms. While clozapine remains unmatched in treatment-resistant cases, Cobenfy provides a promising option, especially for patients with significant negative symptoms.
In psychiatry we are always asking patients about social support. The presence or absence of social support can have a major impact on treatment response and ability to remain well once someone leaves the hospital. This usually includes support from family members and friends.
In 1956 the Medical Research Council Social Psychiatry (MRCSP) London conducted a study regarding the readmission of schizophrenic patients. The research revealed that patients who were stabilized symptomatically and functionally inpatient and subsequently discharged to live with their parents or wives were frequently readmitted for relapse of symptoms compared to those who were discharged to a sibling, or non-family environment. While family involvement is generally a protective factor that helps prevent things like suicide, there are some situations where the over involvement of family can complicate matters and even create worse outcomes.
This usually occurs when a family has high expressed emotion.
Expressed emotion (EE) has consistently been shown to predict relapse in schizophrenia as well as other psychiatric disorders. Expressed emotion is a measure of the family environment that is based on how the relatives of a psychiatric patient spontaneously talk about the patient.
It measures 3 aspects of the family environment associated with high expressed emotion:
Hostility (outward anger and frustration towards the patient because the family believes they are choosing to not get better)
Emotional over-involvement (This is where the family tries to solve all the problems for the patient taking away their ability to be self-reliant).
Critical comments (where the family views the mentally ill patient as lazy or selfish, not appreciating the difficulty of living with mental illness).
However, research has shown the following as indications of an environment with low expressed emotion:
1. Positivity: (statements that express appreciation or support for the patient’s behavior and gives verbal and nonverbal reinforcement).
2. Warmth: (kindness, concern and empathy expressed by the caregiver).
There is such a thing as too much involvement on the part of the families which can lead to complicating family dynamics and exacerbation of an individual’s symptoms of mental illness. Interventions for improving outcomes include reducing contact with high EE caregivers and providing psychoeducation about EE to care givers. Bringing awareness to this behavior may help family members change.
The article “Deprescribing Antipsychotics in Patients with Schizophrenia: Findings from a Specialized Clinic” emphasizes a growing interest in reducing or discontinuing antipsychotic medications in patients with schizophrenia, particularly those stable on long-term treatment. While continuous antipsychotic use is common to prevent relapse, concerns about long-term side effects, such as metabolic give us pause and rise concerns.
Key Points:
Benefits of Deprescribing:
Reduction in side effects such as weight gain and metabolic syndrome.
Potential reversal of tardive dyskinesia.
Empowering patients by involving them in shared decision-making, improving adherence and satisfaction.
Risks:
The primary risk is relapse, with studies indicating relapse rates between 20-60% after discontinuation.
Relapse can lead to hospitalization, job loss, and disrupted relationships.
Strategies for Safe Deprescribing:
Individualized Tapering: Gradual reduction in dose is essential, tailored to the patient’s specific needs and history.
Relapse Prevention: Engaging support systems (family, mental health teams), monitoring for early signs of relapse, and incorporating psychosocial interventions.
Ethical Considerations: Balancing patient autonomy with the duty to minimize harm is a challenge. Encouraging patient participation respects autonomy while ensuring they are aware of risks.
Future Directions:
More research is needed on long-term outcomes of deprescribing, particularly in identifying which patients are the best candidates for safe withdrawal.
Clinical guidelines should better integrate recovery-oriented approaches with deprescribing efforts to strike a balance between risk mitigation and promoting patient empowerment