Tag: medical education

  • Challenges of Antidepressant Management in Primary Care

    Challenges of Antidepressant Management in Primary Care

    Discussions about the potential overprescribing of antidepressants must begin with an understanding of who is doing most of the prescribing. In the U.S., primary care physicians (PCPs) write the majority of antidepressant prescriptions, with estimates suggesting that 60–80% originate from primary care rather than psychiatry (Mojtabai & Olfson, 2011; Mark et al., 2014). This prescribing pattern reflects broader trends in mental health treatment, where primary care has become the frontline for managing depression and other mood disorders.

    Several factors contribute to this dynamic:

    • Limited access to psychiatrists: Many patients, especially in rural or underserved areas, face long wait times or geographic barriers to seeing a psychiatrist.
    • Overlap with medical conditions: PCPs frequently manage conditions like chronic pain, insomnia, and fatigue, for which antidepressants may be considered as part of the treatment plan.
    • Continuity of care: Patients often have longstanding relationships with their primary care providers, making them more comfortable discussing mood symptoms in this setting.
    • Psychiatric referral limitations: Many psychiatrists focus on complex or treatment-resistant cases, meaning initial treatment often falls under primary care.

    Challenges and Considerations

    While primary care plays a crucial role in mental health treatment, concerns exist regarding the effectiveness of antidepressant management in this setting:

    • Suboptimal dosing and medication selection: Studies suggest that antidepressants prescribed in primary care settings may be dosed too low or not adequately adjusted, potentially leading to partial response or treatment failure (Carrasco & Sandner, 2005). Additionally, there is a higher likelihood of using older antidepressants, which may have a less favorable side effect profile.
    • Lack of therapy integration: Guidelines recommend a combination of medication and psychotherapy for moderate-to-severe depression (APA, 2010), yet PCPs may have limited time, training, or referral resources to ensure therapy is included.
    • Potential misdiagnosis: Depressive symptoms can overlap with other psychiatric and medical conditions, leading to misdiagnosis or inappropriate treatment. For example, bipolar disorder is often misdiagnosed as major depressive disorder in primary care, which can result in inadequate treatment and risk of mood destabilization (Hirschfeld et al., 2003).

    Addressing These Challenges

    Several strategies can improve antidepressant management within primary care settings:

    • Collaborative care models: Studies show that integrating mental health professionals within primary care teams leads to improved outcomes, including higher remission rates and better adherence (Archer et al., 2012).
    • Standardized screening and follow-up: Implementing tools like the PHQ-9 for monitoring depression severity can help guide treatment decisions and ensure timely adjustments.
    • Education and decision support: Providing PCPs with continuing education on psychiatric prescribing and decision-support tools can enhance treatment precision.
    • Improved access to therapy: Expanding tele-therapy options and embedding behavioral health providers in primary care clinics can help bridge the gap between medication and psychotherapy.

    Conclusion

    Given the high volume of antidepressant prescriptions originating from primary care, ensuring optimal management is critical to improving patient outcomes. Strengthening collaboration between PCPs and mental health specialists, enhancing diagnostic accuracy, and integrating therapy referrals can help address current limitations.

    Call to Action: If you are a healthcare professional involved in prescribing antidepressants, what strategies have you found effective in improving patient outcomes? Share your insights and experiences below.


  • What Happens When We Ignore Scientific Evidence?

    What Happens When We Ignore Scientific Evidence?

    When we reject the overwhelming scientific consensus that vaccines do not cause autism, we enter a dangerous world—one where facts are disregarded, misinformation thrives, and preventable diseases make a deadly comeback.

    The Real Consequences of Vaccine Hesitancy

    Vaccine hesitancy isn’t just a debate—it has real, measurable consequences

    Measles Outbreaks: In early 2025, Texas experienced its most severe measles outbreak in nearly 30 years, with 198 confirmed cases as of March 7. The outbreak has resulted in 23 hospitalizations and one measles-related death—the first in the nation in a decade. The outbreak is primarily concentrated in rural Gaines County, where vaccination rates are notably low.

    Whooping Cough Resurgence: Cases of pertussis (whooping cough) have increased in areas with lower vaccination rates, endangering infants who are too young to be fully vaccinated.

    Polio’s Return: In 2022, a case of paralytic polio emerged in New York, decades after the disease had been eliminated in the U.S., traced back to vaccine hesitancy and low immunization coverage.

    Ignoring evidence doesn’t just impact individuals—it threatens public health as a whole

    Addressing Concerns: Why the Autism Myth Persists

    Some parents worry about vaccine safety due to outdated or misleading claims, most notably a fraudulent 1998 study linking vaccines to autism. This study was retracted, and extensive research—including studies on hundreds of thousands of children—has confirmed no link between vaccines and autism. Yet, fear and misinformation persist, fueled by social media echo chambers and distrust in institutions.

    While vaccine side effects do exist, they are typically mild (e.g., temporary soreness, fever) and far outweighed by the risks of the diseases they prevent. Scientific inquiry should always continue, but dismissing decades of rigorous research in favor of debunked myths endangers lives.

    What Can We Do?

    Combatting vaccine misinformation requires action. Here’s how you can help

    ✔ Speak Up: Correct misinformation when you see it, whether online or in conversations with friends and family.

    ✔ Rely on Experts: Trust reputable sources like the CDC, WHO, and medical professionals rather than social media influencers or unverified websites.

    ✔ Advocate for Science Education: Supporting critical thinking and scientific literacy helps build a society that values evidence over fear.

    ✔ Get Vaccinated: Lead by example—being up to date on vaccines protects you and those around you, especially vulnerable populations.

    Science Is Not an Opinion

    Truth is not subjective. If we abandon scientific evidence in favor of belief alone, we risk more than just vaccine-preventable diseases—we risk an era where facts no longer matter. The stakes are too high to let misinformation win.

  • 🌿 CBD for Psychosis? A Landmark Trial is Underway 🧠

    🌿 CBD for Psychosis? A Landmark Trial is Underway 🧠

    A major new study—the Stratification and Treatment in Early Psychosis (STEP) trial—is set to investigate CBD as a potential treatment for psychosis on a larger scale than ever before. Led by Philip McGuire, MD, professor of psychiatry at Oxford University, STEP will involve 1,000 participants across 30 sites in 10 countries 🌍, making it one of the most ambitious trials of its kind.

    🔬 Why it matters:
    ✅ CBD has shown promise in early studies for psychosis, but large-scale evidence is needed.
    ✅ STEP will combine three smaller trials to explore effectiveness, biomarkers, and precision treatment approaches.
    ✅ Nature Medicine named it one of 11 studies that will shape medicine in 2025.

    🚀 Could CBD redefine psychosis treatment? The results could change the landscape of psychiatric care. Stay tuned!

  • The Most Commonly Prescribed Medication for Bipolar Disorder… But Is It the Best?

    The Most Commonly Prescribed Medication for Bipolar Disorder… But Is It the Best?

    When it comes to bipolar disorder, the most commonly prescribed medication isn’t necessarily the most effective.Many clinicians default to prescribing quetiapine, valproate, or lamotrigine, yet lithium remains the gold standardfor long-term treatment.

    So, why is lithium often overlooked? Despite decades of evidence supporting its unmatched efficacy in preventing relapse, reducing suicide risk, and stabilizing mood long-term, lithium is underprescribed due to concerns over side effects, monitoring requirements, and physician discomfort with its use.

    🔹 What Do the RCTs Say About Lithium?

    ✅ BALANCE Trial (2010) – The landmark study comparing lithium vs. valproate vs. combination therapy found that lithium monotherapy was superior to valproate in preventing relapse into both manic and depressive episodes (Geddes et al., 2010).

    ✅ NIMH STEP-BD Trial (2005) – Among mood stabilizers, lithium significantly reduced suicide risk, a benefit not shared by other common treatments (Goodwin et al., 2003).

    ✅ Cade’s Legacy and Beyond – Multiple meta-analyses confirm that lithium reduces relapse rates and is the only mood stabilizer with strong anti-suicidal effects (Cipriani et al., 2005).

    🚨 The Bottom Line? Lithium is STILL the most effective long-term treatment for bipolar disorder, yet it is often underutilized. Instead, newer and more expensive alternatives are frequently prescribed—even when they lack lithium’s robust evidence base.

    Yes, lithium requires monitoring. Yes, it comes with side effects. But for patients with bipolar disorder, choosing the right medication can mean the difference between stability and relapse, life and death.

    Let’s start prescribing based on data, not convenience. 🔥

  • The Pill Won’t Solve It All 💊🚫

    The Pill Won’t Solve It All 💊🚫

    When every problem you face has been treated exclusively by a pill, you start to believe that the answer to all your struggles lies in finding the right one. 🤔💡

    With this mindset, you will never be well. 🧠❌

    It’s no different than someone searching for the perfect car 🚗 or the dream home 🏡 to fix their life. Sure, it might bring temporary relief, but in the end, it steals your power, leaving your happiness dependent on external factors you can’t control. 🎭🔗

    True healing starts when you reclaim your own agency. 💪🔥

  • 📌 CANMAT Guidelines for Depression: 2023 Update

    📌 CANMAT Guidelines for Depression: 2023 Update

    The Canadian Network for Mood and Anxiety Treatments (CANMAT) released updated guidelines in 2023 for the management of Major Depressive Disorder (MDD), reflecting recent advancements in the field.

    Key Updates in the 2023 CANMAT Guidelines:

    1. Personalized Care Approach:
      • Emphasis on shared decision-making, considering patient values, preferences, and treatment history to tailor individualized treatment plans.
    2. Updated Treatment Recommendations:
      • Psychological Therapies: Continued endorsement of therapies like Cognitive Behavioral Therapy (CBT) and Interpersonal Therapy (IPT) for mild to moderate depression.
      • Pharmacological Treatments: Introduction of newer antidepressants and updated recommendations based on recent evidence.
      • Neuromodulation: Expanded guidance on treatments such as Transcranial Magnetic Stimulation (TMS)and Electroconvulsive Therapy (ECT), especially for treatment-resistant cases.
    3. Lifestyle and Complementary Interventions:
      • Recognition of the role of exercise, nutrition, and sleep in managing depression.
      • Evaluation of complementary and alternative medicine approaches, providing guidance on their efficacy and safety.
    4. Digital Health:
      • Assessment of digital interventions, including online therapy platforms and mobile applications, as supplementary tools in treatment plans.
    5. Management of Inadequate Response:
      • Strategies for addressing partial or non-response to initial treatments, including augmentation and combination therapies.

    These updates underscore the importance of a collaborative and individualized approach in managing MDD, integrating the latest evidence to optimize patient outcomes.

    For a comprehensive overview, refer to the full publication: 

    pubmed.ncbi.nlm.nih.gov

  • 💊 Are Antidepressants Overprescribed in the U.S.? 🤔

    💊 Are Antidepressants Overprescribed in the U.S.? 🤔

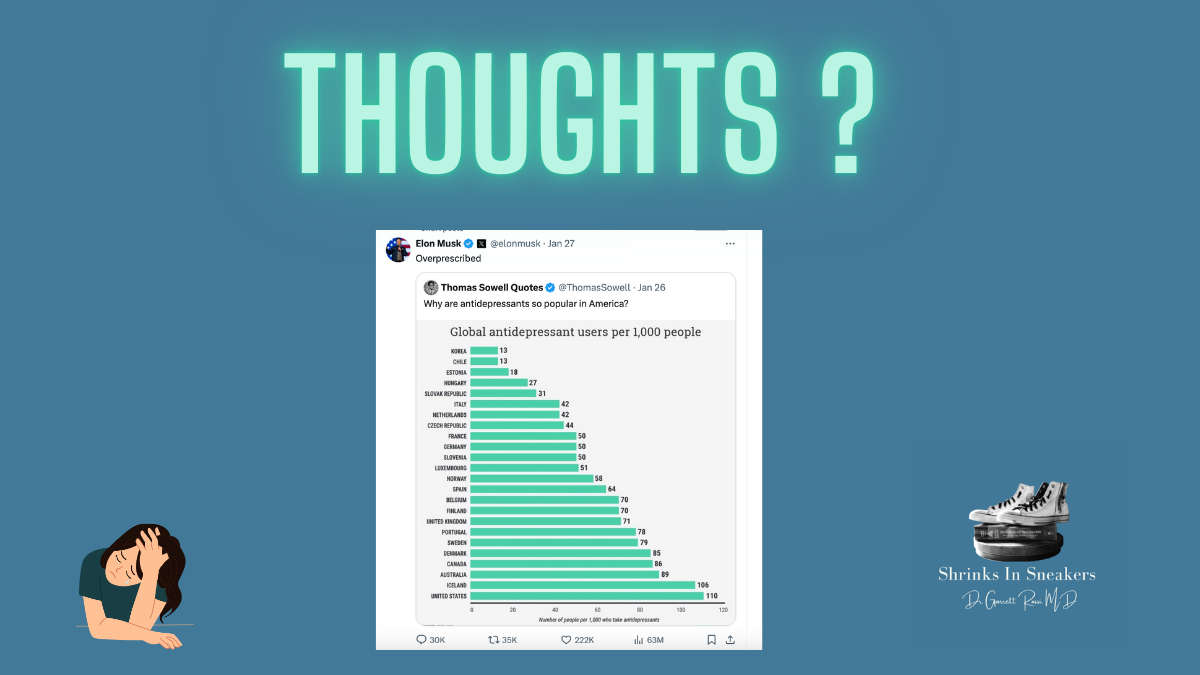
    The question of whether antidepressants are overprescribed in the United States is complex and depends on how “overprescription” is defined.

    Arguments Suggesting Overprescription

    1. Broad Diagnostic Criteria:
      • The criteria for diagnosing conditions like major depressive disorder (MDD) can be broad, potentially leading to overdiagnosis and, consequently, overprescription.
    2. Prescribing Practices:
      • Primary care physicians write most antidepressant prescriptions, often without thorough psychiatric evaluation.
      • Some prescriptions are written for mild cases of depression or subclinical symptoms where psychotherapy or lifestyle changes might suffice.
    3. Off-Label Use:
      • Antidepressants are frequently prescribed off-label for conditions like insomnia, chronic pain, or anxiety, contributing to their high utilization.
    4. Pharmaceutical Influence:
      • Aggressive marketing by pharmaceutical companies has historically played a role in increasing antidepressant use.

    Arguments Against Overprescription

    1. Underdiagnosis and Undertreatment:
      • Despite high prescription rates, many individuals with diagnosable depression or anxiety disorders go untreated, particularly in underserved populations.
      • Stigma and access barriers often prevent people from seeking care.
    2. Increasing Mental Health Awareness:
      • Growing awareness of mental health issues may explain rising prescription rates, as more people seek help for legitimate conditions.
    3. Non-Psychiatric Indications:
      • Antidepressants are also effective for non-depressive disorders, like obsessive-compulsive disorder (OCD), post-traumatic stress disorder (PTSD), and chronic pain, which justifies some of their broader use.

    Data on Antidepressant Use

    According to surveys, about 1 in 8 Americans aged 18 and older take antidepressants, and usage is particularly high among women, especially those aged 40–59. While this might seem like a high prevalence, it may also reflect greater recognition and treatment of mental health issues.

    Key Considerations

    • Patient-Centered Care: The decision to prescribe antidepressants should be tailored to the individual, based on a comprehensive assessment of their symptoms and needs.
    • Access to Alternatives: Many individuals lack access to evidence-based non-pharmacological treatments like psychotherapy due to cost, availability, or stigma, making antidepressants a more feasible option.
    • Role of Education: Educating both prescribers and patients on appropriate use can reduce potential overprescription.
  • Breaking the Anxiety Barrier: LSD a Game-Changer for GAD?

    Breaking the Anxiety Barrier: LSD a Game-Changer for GAD?

    Should LSD be considered a treatment for generalized anxiety disorder (GAD)? The results from MindMed’s Phase 2b study suggest it just might be. While this is only one study, and the FDA’s cautious stance on psychedelic-based treatments like MDMA raises questions about future approval, the findings are worth exploring. So, let’s dive in.

    GAD is a fascinating and somewhat controversial diagnosis. Notably, the study excluded participants with major depressive disorder, a condition frequently comorbid with GAD, which raises interesting questions about the choice to isolate GAD. Some in the psychiatric field even challenge the validity of GAD as a distinct psychiatric disease, arguing it reflects broader distress rather than a discrete disorder.

    Psychedelics like LSD are surging to the forefront of psychiatric research, largely because the field is starved for innovation. Decades of research and sophisticated drug development have yielded limited breakthroughs in understanding or treating psychiatric conditions. Meanwhile, society often clings to the hope that complex human behavior and mental health challenges can be reduced to something as simple as a pill you take every 12 weeks. The appeal of psychedelics lies in their potential to disrupt this paradigm—but can they deliver?

    Key Findings:

    1. Dose-Dependent Response:
      • Patients receiving a higher dose (200 µg) of MM-120 showed rapid and sustained improvements in anxiety symptoms.
      • The reduction in anxiety symptoms was statistically significant compared to the placebo group.
    2. Speed of Onset:
      • Improvements were observed as early as two weeks post-dosing, suggesting a rapid therapeutic effect.
    3. Duration of Effect:
      • The anxiety-reducing effects lasted up to 12 weeks following a single administration, indicating long-lasting benefits.
    4. Safety Profile:
      • The treatment was generally well-tolerated, with mild to moderate adverse effects such as headache, nausea, and transient emotional changes. There were no reports of severe adverse events related to the study drug.
    5. Mechanistic Insights:
      • MM-120 appears to modulate serotonin 5-HT2A receptors, leading to enhanced neuroplasticity and emotional processing, which may underlie the observed clinical improvements.

    I’m always interested in the study population and if the researchers selected a group of patients with prior psychedelic use. Here is what I found 

    Participant Screening and Inclusion:

    1. Prior Psychedelic Use:
      • Some participants may have had previous experiences with psychedelics (e.g., LSD, psilocybin, MDMA), as long as such use did not interfere with the integrity of the study (e.g., recent or habitual use, which might influence tolerance or expectations).
      • Individuals with significant past psychedelic use might be excluded to minimize potential biases in response to the trial drug.
    2. Psychedelic-Naïve Participants:
      • The trial likely included a substantial proportion of participants who were psychedelic-naïve, meaning they had never used substances like LSD or psilocybin before.
      • This approach helps ensure that the observed therapeutic effects can be attributed to MM-120 rather than prior familiarity or psychological preparation for psychedelic experiences.

    Why Prior Use Matters:

    • Expectation Bias:
      • Participants with past psychedelic experiences may anticipate certain effects, influencing subjective outcomes like anxiety reduction.
    • Safety and Tolerability:
      • Previous exposure to psychedelics might affect how participants tolerate or respond to the treatment.
    • Generalizability:
      • Including both psychedelic-naïve and experienced individuals helps make the findings applicable to a broader population.

    Implications:

    This study suggests that psychedelic-assisted therapy, especially with compounds like MM-120, has significant potential as a novel treatment for GAD, offering rapid and durable relief after just one dose. These findings pave the way for further research and larger-scale trials.

  • Psychiatry: Ahead of the Curve on Singulair’s Neuropsychiatric Risks

    Psychiatry: Ahead of the Curve on Singulair’s Neuropsychiatric Risks

    Psychiatry is often criticized for being “late to the table” when it comes to recognizing the broader impacts of medical treatments. However, in the case of Singulair (montelukast), psychiatry has been aware of its potential neuropsychiatric effects for quite some time.

    Singulair, widely used for asthma and allergic rhinitis, has long been associated with side effects such as mood changes, anxiety, depression, and even suicidality. This connection has been documented for years, yet the broader medical community and regulatory bodies have taken time to fully address these risks.

    Recently, the FDA issued a new warning aimed at heightening awareness of montelukast’s neuropsychiatric side effects. This update emphasizes the importance of assessing the risk-benefit ratio, particularly for patients with mild conditions where alternative treatments may suffice.

    Psychiatry’s Role

    Psychiatrists have long recognized and documented cases where montelukast seemed to exacerbate or trigger psychiatric symptoms. Many of us have seen patients whose mood instability or new-onset anxiety correlated with starting the medication, leading to its discontinuation and subsequent symptom improvement.

    Why This Matters

    This development underscores the value of psychiatry’s vigilance in identifying patterns that might initially go unnoticed in other fields. It’s also a reminder of the importance of collaboration between specialties to ensure patient safety.

    Key Takeaways:

    • Patients and families: Be aware of the potential neuropsychiatric side effects of montelukast. Monitor mood, sleep, and behavior changes closely, especially in children.
    • Clinicians: Always evaluate the necessity of montelukast in mild cases and consider alternatives when possible. Open conversations with patients about these risks can be life-saving.
    • Psychiatrists: Continue advocating for the recognition of neuropsychiatric risks in non-psychiatric medications. Our input is crucial in ensuring patient safety.

    Psychiatry wasn’t late to this table. In fact, we may have set it.

  • The Silent Crisis: Physician Suicide in the United States

    The Silent Crisis: Physician Suicide in the United States

    I saw these magnets today on the refrigerator located in the physicians lounge and it seemed like a good reminder 

    In the U.S., an estimated 300-400 physicians die by suicide each year, a staggering rate far higher than that of the general population. This crisis, largely unspoken in healthcare settings, underscores the immense pressures physicians face daily. The high expectations, long hours, emotional exhaustion, and the stigma around seeking mental health support create a dangerous environment where burnout can quickly spiral into severe mental health struggles.

    Physicians are trained to endure, often putting others’ health before their own. But the costs of “pushing through” take a toll. Many feel they cannot safely reach out for help without risking their careers due to institutional stigma around mental health treatment. This cycle of isolation and suppressed emotion can lead to tragic outcomes.

    Organizations are beginning to address this issue by implementing wellness programs, peer support systems, and confidential mental health resources, but more systemic changes are needed. Reducing the stigma around mental health support, reforming punitive policies, and fostering a culture of openness in medicine could be life-saving.

    Physician suicide affects us all—it robs the healthcare system of dedicated professionals and leaves profound impacts on patients, families, and communities. It’s time to break the silence and actively support those who care for us.